0

Virtual Reality Simulated Patient Encounters

Reset

TCCC Blast Injury with ARSC

In partnership with: VALOR Program

Book Demo

Scenario Description

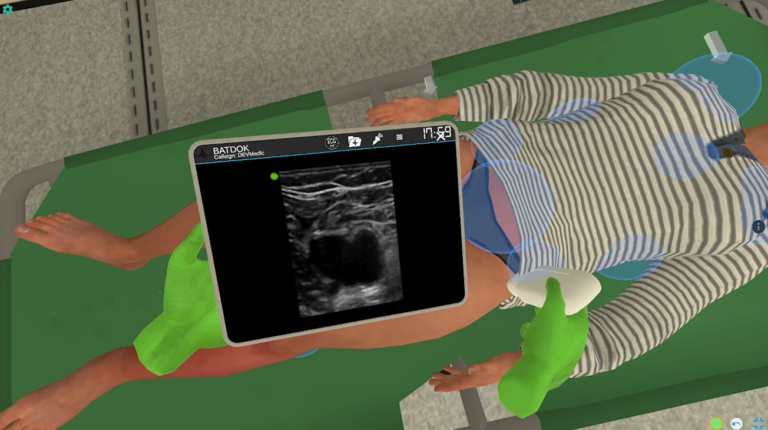
The scenario begins in a building of opportunity, evaluating a casualty immediately after being brought in by a medic following a dismounted blast injury. The casualty sustained a left below-the-knee traumatic amputation, a left upper extremity amputation, and penetrating trauma to the abdomen. There is no significant chest trauma. A FAST is positive for free fluid in RUQ and LUQ views. Providers should continue MARCH assessment, provide life-saving interventions such as blood transfusions. The casualty continues to decline and the surgical team members should continue ongoing damage control resuscitation, including initiating massive transfusion, giving TXA, giving calcium gluconate IV, and performing damage control abdominal laparotomy. If managed appropriately, the patient will stabilize and can be prepared for transport.

Learning Objectives

1. Rapidly recognize the need for early damage control resuscitation.
2. Determine risk for massive transfusion, defined as the need for 10 or more units of red blood cells / whole blood within the first 24 hours.
3. Initiate warmed whole blood transfusion as close to the time-of injury as possible.
4. Optimize patient’s ionized calcium, and prevent hypocalcemia related to massive transfusion.
5. Understand that calcium gluconate is preferred for peripheral IV administration.
6. Optimize the patient’s magnesium level if results are available, and complete replacement in the setting of massive transfusion and severe hypocalcemia.
7. For casualties at high risk of hemorrhagic shock, demonstrate administration of TXA 2g IV/IO within three hours of injury.
8. Determine the risk of coagulopathy during massive transfusion.
9. Demonstrate appropriate hypothermia prevention by warming the casualty with available resources.
10. Demonstrate the ability to stabilize and prepare patients for casualty evacuation.
11. In prolonged casualty care situations, document urine output as a valuable indicator for adequate resuscitation from hemorrhagic shock.
12 Understand appropriate endpoints for resuscitation.
13. Understand that if casualty is not responsive to resuscitative efforts despite adequate resuscitation, either additional resuscitation and/or hemorrhage control interventions are needed, or the injury is not survivable given resources and capabilities available.
14. Understand that it is best to avoid use of crystalloid in pre-hospital settings and instead use blood products for resuscitation.
15. Understand that it is best practice to avoid use of vasopressors in hemorrhagic shock.
16. Understand that it is best practice to avoid use of hypertonic saline in hemorrhagic shock, which should only be used for patients with TBI and evidence/suspicion of raised intracranial pressure.
17. Demonstrate appropriate airway management and obtain oral endotracheal intubation or surgical cricothyrotomy when indicated.

MINIMUM:

OS: Windows 10
Processor: Intel Core i5-2300 | AMD FX-4350
Memory: 4 GB RAM
Graphics: Nvidia GeForce GTX 2060
DirectX: Version 11
Storage: 12 GB available space

RECOMMENDED:

OS: Windows 10
Processor: Intel Core i7-2300 | AMD FX-4350
Memory: 8 GB RAM
Graphics: Nvidia GeForce GTX 3060
DirectX: Version 11
Storage: 12 GB available space

You Don’t Have to Figure Out VR Alone

Our Team Clinicians Will Guide Every Step
Expert education, support, and curriculum integration services are available for this scenario by trained educators and clinicians.
Explore Solutions

“I would recommend SimX VR technology to anyone.”

Jenny Patton CEHRS Manager of Medical Training Platforms